Advertisement
Advertisement
September 2026 Supplement
Sponsored by Cagent Vascular
Serration, Not Dissection: A New Paradigm for Luminal Gain in BTK Endovascular Intervention
A distinct approach to vessel preparation or definitive therapy in BTK arterial occlusive disease.
Lower extremity peripheral artery disease (PAD) affects more than 230 million people worldwide, and its prevalence continues to rise as the global population ages. In the United States, approximately 12.5 million individuals are affected1,2; of these, roughly 11% progress to chronic limb-threatening ischemia (CLTI),3 the end stage of PAD, which carries a poor prognosis and high rates of limb loss. Within this subgroup of approximately 1.4 million patients, the annual amputation rate among nondiabetic individuals is approximately 0.17 per 1,000, and among patients with diabetes mellitus, the total annual amputation rate rose from 3 per 1,000 in 2009 to 4.5 per 1,000 in 2015.4
Revascularization is therefore essential in CLTI to limit tissue loss and preserve a functional limb. Because these patients frequently have multilevel disease, the optimal strategy is direct revascularization that re-establishes straight in-line flow to the foot. When no such option exists, indirect revascularization that maximizes perfusion to the wound angiosome through collateral pathways is an acceptable alternative.5 Revascularization options include percutaneous endovascular intervention, open surgical bypass or endarterectomy, or a hybrid approach that combines percutaneous endovascular intervention and surgery, performed either concomitantly or in a staged fashion. Ultimately, successful CLTI management depends on a collaborative, multispecialty approach aimed at complete wound healing, minimal tissue loss, and preservation of ambulatory status.
"The Serranator mechanistically brings a distinct approach to vessel preparation or definitive therapy in BTK arterial occlusive disease."
DILATING THE STENOTIC VESSEL
The endovascular treatment of PAD began on January 16, 1964, when Dr. Charles Dotter used a coaxial catheter to dilate a stenosed left superficial femoral artery (SFA) in an 82-year-old woman with severe rest pain and gangrene, the historical equivalent of Rutherford category 5 CLTI.6 A decade later, on February 12, 1974, Dr. Andreas Grüntzig applied a nonelastic PVC balloon-tipped catheter to open a severely stenosed femoral artery, and further miniaturization of that balloon led to the first percutaneous transluminal coronary angioplasty on September 16, 1977.7
Mechanistically, balloon angioplasty enlarges the lumen through controlled mechanical injury: fracture or rupture of the plaque, dissection of the plaque from the underlying tunica media, and stretching of the tunica media and adventitia. It does not remove plaque—luminal disruption, not debulking, is the dominant mechanism of luminal gain. As a result, plain old balloon angioplasty (POBA) is limited by inherent mechanical problems, including acute elastic recoil, vessel wall dissection, and neointimal hyperplasia that drives restenosis.8 The clinical consequences of these limitations vary substantially by vascular bed and are worse in the infrapopliteal, below-the-knee (BTK) arteries,9 which are small in caliber and, particularly in patients with CLTI, often diffusely diseased and calcified over long segments. Despite these shortcomings and the emergence of alternatives, POBA remains the standard of care for primary endovascular treatment of infrapopliteal occlusive disease. Several newer devices and definitive therapeutic options are becoming more widely available, including the use of atherotomy balloons, atherectomy devices, intravascular lithotripsy (IVL), drug-coated balloons (DCBs), drug-eluting stents, and bioresorbable drug-eluting scaffolds, both polymer-based and iron-based.
"Atherotomy" balloon angioplasty refers to balloon-based plaque modification in which specialized elements on the balloon surface make discrete, controlled incisions into atherosclerotic or fibrocalcific plaque during inflation. The term literally means an incision into an artery at the site of atheromatous plaque: the suffix "-tomy" denotes cutting or incision, in contrast to the more familiar "-ectomy," which denotes removal of the atheromatous material. Whereas conventional POBA relies on uniform circumferential wall stress and risks uncontrolled, flow-limiting dissection, an atherotomy balloon creates focal, predictable dissection planes at predetermined points.
These plaque-modifying balloons encompass both cutting and scoring balloons. Cutting balloons carry microsurgical blades (atherotomes) mounted longitudinally on a noncompliant balloon, which incise the plaque as the balloon expands. Scoring balloons are semicompliant or noncompliant balloons fitted with rigid external elements, typically nitinol wires, polymer rails, or raised metal edges arranged along the outer surface, that concentrate radial force along discrete lines to score the plaque during inflation. Because these elements focus the dilating force at a few predetermined points rather than distributing it uniformly around the circumference, the approach is also described as "focal force angioplasty," with controlled dissection as its intended result. Representative devices of this subtype include AngioSculpt® (Philips), Chocolate® (Medtronic), and UltraScore® (BD) balloons.
Serration Remodeling Therapy (SRT) using the Serranator® PTA Serration Balloon Catheter (Cagent Vascular) is a newer and mechanistically distinct therapy for CLTI that uses embedded metal serration strips to create linear rows of micro-fissures in the plaque. Serranator achieves optimal luminal gain at lower inflation pressure, reduction in elastic recoil, and mitigation of the complications associated with POBA.
CASE 1
Case Presentation
A male patient in his mid-60s presented with long-standing bilateral lower extremity PAD complicated by CLTI. PAD was first diagnosed following coronary artery bypass grafting (CABG), and he subsequently underwent multiple percutaneous endovascular interventions for BTK occlusive disease in both lower extremities. Despite these interventions, he required amputation of the right first and second toes and the left first toe. Additional comorbidities included coronary artery disease status post CABG, hypertension, type 2 diabetes mellitus, hyperlipidemia, and end-stage renal disease treated with renal transplantation. He developed a wound on the left fourth toe that failed to heal, with coexisting toe deformities contributing to the delayed healing. He was referred for peripheral angiography and percutaneous endovascular intervention, if clinically indicated, for limb preservation (Rutherford category 5).
Procedural Overview
Antegrade vascular access was obtained in the left common femoral artery (CFA). Baseline angiography demonstrated patent above-the-knee inflow vessels without significant obstructive disease. The left anterior tibial (AT) artery was totally occluded in its proximal segment. The tibioperoneal trunk (TPT) was patent and free of significant disease, supplying a patent left peroneal artery that was likewise free of significant obstruction. The left posterior tibial (PT) artery was patent but harbored a complex, tubular, high-grade (80%-90%) stenosis involving the ostium and proximal segment (Figure 1). Fluoroscopy demonstrated heavy calcification along the course of all three tibial vessels. The access sheath was then exchanged for a 6-F, 45-cm Destination® guiding sheath (Terumo Interventional Systems), which was advanced antegradely with its tip positioned in the P2 segment of the left popliteal artery.
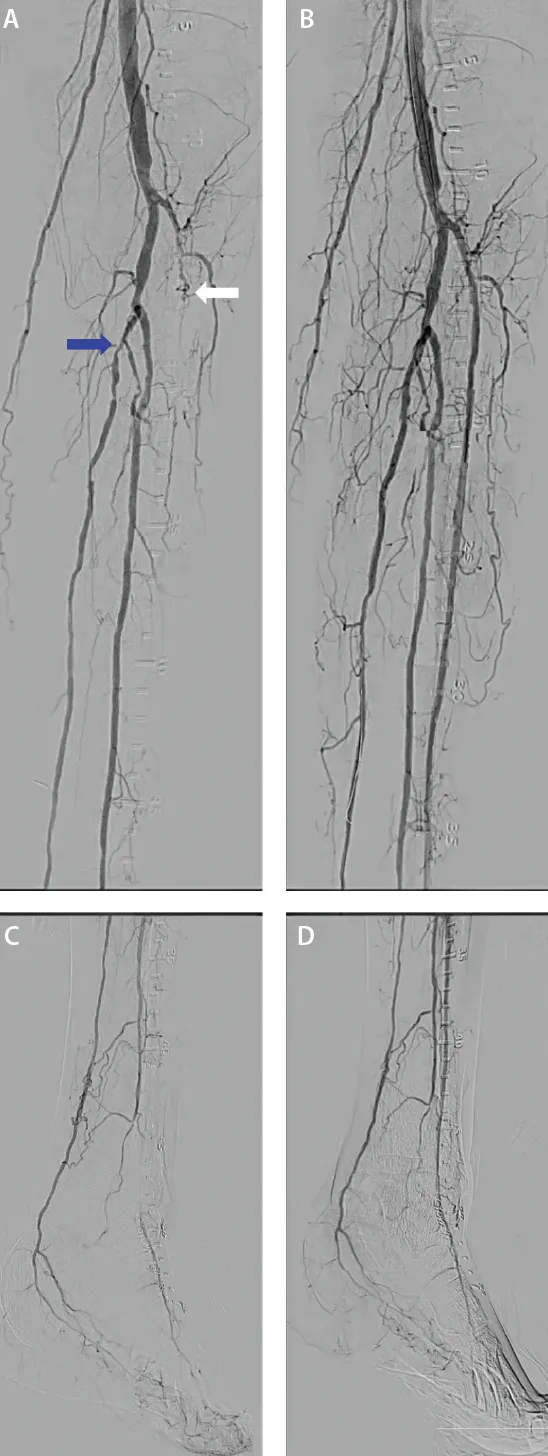
Figure 1. Baseline angiography of left BTK arteries (A) and of the distal pedal vessels (C) showing a totally occluded left AT artery (white arrow, A) and left PT artery with proximal high-grade stenosis (blue arrow, A). Postintervention angiography showing re-establishment of three-vessel runoff to the periphery (B, D).
Unfractionated heparin was administered, with supplemental doses given to maintain an activated clotting time (ACT) above 250 seconds. A 0.014-inch Hi-Torque Command™ 14 guidewire (Abbott Vascular) was successfully advanced across the occluded left AT artery and positioned distally. Given the extent of calcification, vessel preparation ("lesion modification") was undertaken to optimize luminal gain. The guidewire was exchanged for a 0.014-inch ViperWire Advance™ (Abbott Vascular), and orbital atherectomy was performed with a Diamondback 360® peripheral 1.5-mm solid crown (Abbott Vascular). Multiple passes were made at up to 120,000 rpm for a total treatment time of 2 minutes and 35 seconds. Adjunctive SRT was then performed with a 2.5- X 120-mm Serranator PTA Serration Balloon to dilate the recanalized AT artery (Figure 2A and 2B).
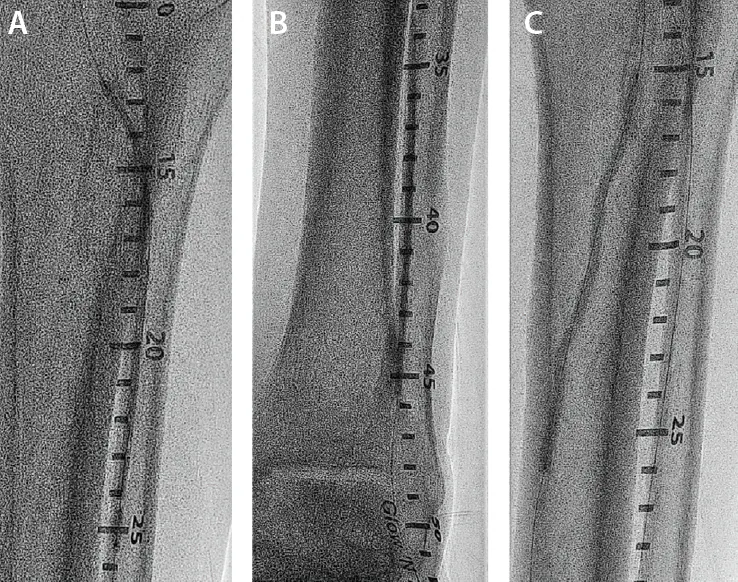
Figure 2. Serranator balloon inflation at the proximal (A) and distal (B) segment of the left AT artery and the proximal segment of the left PT artery (C).
Attention was then turned to the left PT artery. A 0.014-inch Hi-Torque Whisper™ ES guidewire (Abbott Vascular) was advanced across the ostial and proximal stenoses. A 2.5- X 80-mm Shockwave E8 peripheral IVL catheter (Shockwave Medical, a Johnson & Johnson MedTech company) was used to deliver 80 pulses at 4 atm, achieving effective modification of the heavily calcified segments. The same 2.5- X 120-mm Serranator balloon used previously was then used for further dilatation, followed by a 3.0- X 120-mm Sterling® balloon catheter (Boston Scientific Corporation), with an excellent angiographic result.
Final angiography demonstrated excellent dilatation of all treated segments with no significant residual stenosis and brisk flow to the distal vessels (Figure 1B and 1D). With continued close follow-up in the wound clinic, complete wound healing was achieved.
Case 2
Case Presentation
The patient is a male in his mid-70s with longstanding hypertension, type 2 diabetes mellitus with peripheral neuropathy (HbA1c, 6.7%), hyperlipidemia, paroxysmal atrial fibrillation on apixaban 5 mg twice daily, remote cerebrovascular accident without residual neurologic deficit, and lower extremity PAD. He had no history of coronary artery disease and had never smoked. He was referred with ischemic rest pain of the right foot, occurring at night while supine (Rutherford category 4), after an unsuccessful attempt elsewhere to recanalize a totally occluded three-vessel right BTK arterial system. A month later, he underwent successful recanalization of the occluded right peroneal and AT arteries with peripheral excimer laser atherectomy (PELA) and balloon angioplasty and was discharged home improved on clopidogrel 75 mg daily in addition to apixaban. Unfortunately, his nocturnal rest pain recurred approximately 3 to 4 months later, consistent with recurrent Rutherford category 4 ischemia.
Procedural Results
Vascular access was obtained in the right CFA using antegrade approach. Baseline angiography demonstrated a patent right SFA lined by nitinol self-expanding stents along its entire length, with a patent right deep femoral artery showing only mild disease. The right popliteal artery was patent with diffuse mild disease. The right AT artery was totally occluded, and the TPT was occluded proximally with resultant total occlusion of both the right PT and peroneal arteries. Bridging collaterals reconstituted the distal right peroneal artery, which continued as single-vessel runoff to the foot (Figure 3). The femoral access sheath was then exchanged for a 6 F, 45-cm Flexor® Ansel-0 sheath (Cook Medical), which was advanced antegradely with its tip positioned in the mid-P2 segment of the right popliteal artery.
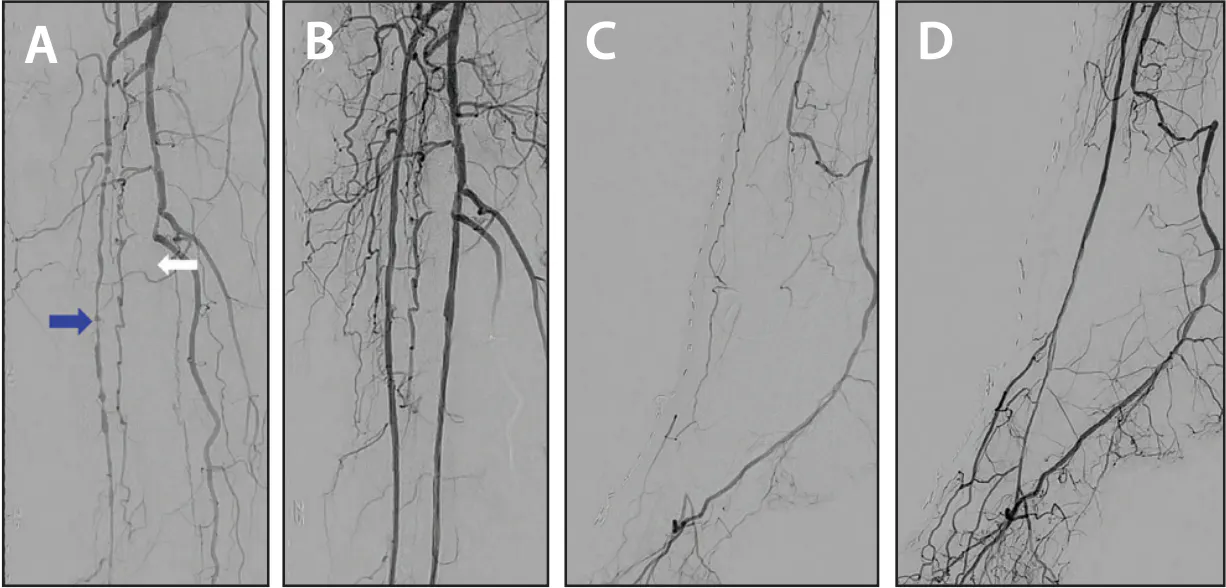
Figure 3. Baseline angiography of right BTK arteries (A) and of the distal pedal vessels (C) showing a totally occluded right AT artery (blue arrow, A) and totally occluded right peroneal artery (white arrow, A). Postintervention angiography showing re-establishment of two-vessel runoff to the periphery (B, D).
Intravenous anticoagulation was achieved with unfractionated heparin, with supplemental doses administered to maintain an activated clotting time above 250 seconds. The totally occluded right peroneal artery was crossed with a 0.014-inch Hi-Torque Command 14 guidewire, which was then exchanged for a 0.014-inch Hi-Torque Spartacore® guidewire (Abbott Vascular). PELA was performed with a 1.4-mm Turbo-Elite® laser atherectomy catheter (Philips), initially at 45 mJ/mm2 and 25 Hz and then at 60 mJ/mm2 and 40 Hz, for a total of 15,375 pulses over a treatment time of 6 minutes and 58 seconds, successfully recanalizing the occluded vessel. The recanalized segment was predilated with a 1.5–2.0- X 210-mm NanoCross™ Elite PTA balloon catheter (Medtronic). SRT was then performed with a 2.5- X 120-mm Serranator PTA Serration Balloon, with an excellent angiographic result.
With flow re-established through the recanalized right peroneal artery, a 0.014-inch Fielder® XT guidewire (Asahi Intecc) was advanced through the communicating (calcaneal) branch of the peroneal artery into the distal right PT artery and onward into the lateral plantar artery (Figure 4A). The wire was tracked distally around the pedal-plantar loop, where the lateral plantar artery joins the deep plantar branch of the dorsalis pedis artery (DPA; Figure 4B) and then retrogradely up the right DPA (Figure 4C). The Fielder XT was exchanged for a 0.014-inch Approach® CTO microwire (Cook Medical), which was advanced retrogradely through the totally occluded right AT artery and captured within a 0.018-inch support catheter positioned in the proximal vessel, thereby completing the transpedal retrograde crossing. After exchange for a 0.014-inch Spartacore guidewire, PELA of the AT artery was performed with a 1.4-mm Turbo-Elite laser atherectomy catheter, initially at 45 mJ/mm2 and 25 Hz and then at 60 mJ/mm2 and 40 Hz, for a total of 12,886 pulses over 6 minutes and 31 seconds. Definitive SRT was delivered with a 2.5- X 120-mm Serranator PTA Serration Balloon. Final angiography demonstrated pulsatile, straight, in-line flow from the patent right SFA and popliteal arteries through the TPT into two-vessel runoff (right AT and peroneal arteries) to the foot (Figure 4D).
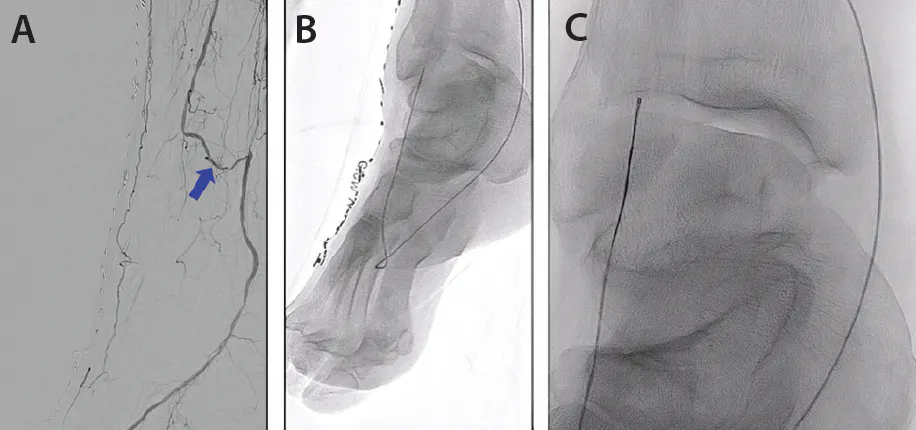
Figure 4. Communicating (calcaneal) branch of the right peroneal artery into the distal right PT artery (A). Guidewire advanced from the right peroneal artery and into the lateral plantar artery of the right PT artery and around the pedal-plantar loop (B). Guidewire advanced retrogradely up the right DPA into a 0.018‑inch support catheter in the right AT artery (C).
Postprocedure Results
Laboratory workup during the admission identified the patient as a clopidogrel nonresponder, with a platelet reactivity of 231 P2Y12 reaction units while on therapy. He was discharged home on ticagrelor 90 mg twice daily and apixaban 5 mg twice daily. There was complete resolution of his resting foot pain and there was no recurrence on his 9-month clinic visit.
DISCUSSION
Infrapopliteal disease in patients with CLTI remains the most demanding territory in peripheral intervention. The vessels are small, the lesions are long and frequently occlusive, and calcification is the rule rather than the exception. Balloon angioplasty, the foundation of endovascular therapy since Dotter and Grüntzig, achieves luminal gain through uncontrolled vessel injury, and its limitations of elastic recoil, flow-limiting dissection, and restenosis are most consequential precisely where the margin for error is smallest. The evolution from POBA to plaque modification reflects a shift in philosophy: rather than overpowering the lesion with pressure, the aim is to alter its mechanical properties in a controlled, predictable fashion so that the vessel yields along predetermined lines.
The two cases presented illustrate how SRT fits within this framework. In each instance, serration angioplasty delivered a smooth, well-expanded lumen with controlled dissection and without the need for bailout stenting, preserving future options in vessels that may require reintervention. The second case additionally highlights the value of the transpedal retrograde approach through the pedal-plantar loop when antegrade crossing fails and the critical reappraisal of antiplatelet therapy when early recurrence occurs, with the discovery of clopidogrel nonresponse and transition to ticagrelor. Case 1 progressed to complete wound healing. On a 9-month clinic visit, the Case 2 patient remained asymptomatic with duplex ultrasound–confirmed patency.
These procedural observations are consistent with the prospective, single-arm, multicenter PRELUDE-BTK study, in which serration angioplasty of 53 infrapopliteal lesions in 46 patients achieved a mean final residual stenosis of 21.8% and a mean luminal gain of 1.55 mm at a mean maximum inflation pressure of only 6 atm, with a bailout stent rate of 1.9%, no device-related serious adverse events, and 97.7% freedom from clinically driven target lesion revascularization at 6 months; intravascular imaging in a subset confirmed the serration effect in every lesion examined.10 Those results, like the two cases described here, describe procedural and early clinical success. They support a practical principle for the interventionalist treating CLTI: in the BTK arteries, the quality of the result depends less on any single device than on a thoughtful, lesion-specific sequence of crossing, vessel preparation, and definitive dilatation, delivered within a collaborative, multispecialty program whose measures of success are wound healing, limb preservation, and a patient who continues to walk.
Beyond acute luminal gain, plaque modification has a second rationale: it may improve the delivery of antiproliferative drug when a DCB is used as definitive therapy. Paclitaxel and sirolimus must diffuse from the balloon surface into the media to inhibit neointimal hyperplasia, and calcified plaque acts as a physical barrier to that transfer.
In an ex vivo human peripheral artery model, Tzafriri et al demonstrated that calcification markedly reduced paclitaxel diffusivity and tissue retention, and that orbital atherectomy of the calcified plaque restored drug penetration toward that of noncalcified vessel.11 Computational modeling has since predicted that drug concentration in calcified wall segments can be orders of magnitude lower than in adjacent healthy tissue.12 By fracturing, incising, or debulking calcium and creating controlled cleavage planes through the plaque, vessel preparation is therefore hypothesized to expose the media to the drug, in addition to permitting full balloon expansion at lower pressure with fewer flow-limiting dissections.
Clinical confirmation of this hypothesis has been uneven. In the femoropopliteal segment, the randomized Disrupt PAD III trial of IVL versus plain balloon predilatation before DCB in calcified lesions showed higher procedural success, fewer flow-limiting dissections (1.4% vs 6.8%), and less bailout stenting (4.6% vs 18.3%) with IVL, and this translated into superior primary patency at 1 year (80.5% vs 68.0%) and 2 years (74.4% vs 57.7%).13,14 By contrast, the DEFINITIVE AR pilot trial of directional atherectomy before DCB found improved technical success but no significant difference in 12-month patency compared with DCB alone (84.6% vs 81.3%), although the study was underpowered.15 The only BTK randomized comparison of atherectomy plus DCB versus DCB alone in long infrapopliteal lesions did not demonstrate a significant patency advantage,16 and no randomized trial has yet tested serration or scoring angioplasty as preparation for DCB in tibial vessels. The concept is thus biologically well founded and clinically validated for IVL in the calcified femoropopliteal artery, but for the BTK arteries, it remains a rational strategy awaiting prospective confirmation.
CONCLUSION
SRT with the Serranator PTA Serration Balloon mechanistically brings a distinct approach to vessel preparation or definitive therapy in BTK arterial occlusive disease. The embedded external serrated metal strips on the semicompliant balloon creates “controlled” longitudinal micro-fissures rather than the dissection planes, which are very random, that is associated with conventional balloon dilatation of the atheromatous plaque.
1. McDermott MM, Ho KJ, Alabi O, et al. Disparities in diagnosis, treatment, and outcomes of peripheral artery disease: JACC scientific statement. J Am Coll Cardiol. 2023;82:2312-2328. doi: 10.1016/j.jacc.2023.09.830
2. Zhou J, Liu X, Shan S, et al. Global, regional, and national prevalence of peripheral arterial disease in 2023: an updated systematic review and modelling study. Lancet Glob Health. 2026;14:103983. doi: 10.1016/j.langlo.2026.103983
3. Nehler MR, Duval S, Diao L, et al. Epidemiology of peripheral arterial disease and critical limb ischemia in an insured national population. J Vasc Surg. 2014;60:686-95.e2. doi: 10.1016/j.jvs.2014.03.290
4. Criqui MH, Matsushita K, Aboyans V, et al. Lower extremity peripheral artery disease: contemporary epidemiology, management gaps, and future directions: a scientific statement from the American Heart Association. Circulation. 2021;144:e171-e191. doi: 10.1161/CIR.0000000000001005
5. Gornik HL, Aronow HD, Goodney PP, et al. 2024 ACC/AHA/AACVPR/APMA/ABC/SCAI/SVM/SVN/SVS/SIR/VESS guideline for the management of lower extremity peripheral artery disease: a report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice. Circulation. 2024;149:e1313-e1410. doi: 10.1161/CIR.0000000000001251
6. Friedman SG. Charles Dotter and the fiftieth anniversary of endovascular surgery. J Vasc Surg. 2015;61:556-558. doi: 10.1016/j.jvs.2014.09.012
7. Barton M, Grüntzig J, Husmann M, Rösch J. Balloon angioplasty–the legacy of Andreas Grüntzig, M.D. (1939–1985). Front Cardiovasc Med. 2014;1. https://doi.org/10.3389/fcvm.2014.00015
8. Byrne RA, Stone GW, Ormiston J, et al. Coronary balloon angioplasty, stents, and scaffolds. Lancet. 2017;390:781-792. doi: 10.1016/S0140-6736(17)31927-X
9. Giannopoulos S, Varcoe RL, Lichtenberg M, et al. Balloon angioplasty of infrapopliteal arteries: a systematic review and proposed algorithm for optimal endovascular therapy. J Endovasc Ther. 2020;27:547-564. doi: 10.1177/1526602820931488
10. Holden A, Lichtenberg M, Nowakowski P, et al. Prospective study of serration angioplasty in the infrapopliteal arteries using the Serranator device: PRELUDE BTK study. J Endovasc Ther. 2022;29:586-593. doi: 10.1177/15266028211059917
11. Tzafriri AR, Garcia-Polite F, Zani B, et al. Calcified plaque modification alters local drug delivery in the treatment of peripheral atherosclerosis. J Control Release. 2017;264:203-210. doi: 10.1016/j.jconrel.2017.08.037
12. Colombo M, Corti A, Berceli S, et al. 3D modelling of drug-coated balloons for the treatment of calcified superficial femoral arteries. PLoS One. 2021;16:e0256783. doi: 10.1371/journal.pone.0256783
13. Tepe G, Brodmann M, Werner M, et al. Intravascular lithotripsy for peripheral artery calcification: 30-day outcomes from the randomized Disrupt PAD III trial. JACC Cardiovasc Interv. 2021;14:1352-1361. doi: 10.1016/j.jcin.2021.04.010
14. Tepe G, Brodmann M, Bachinsky W, et al. Intravascular lithotripsy for peripheral artery calcification: mid-term outcomes from the randomized Disrupt PAD III trial. J Soc Cardiovasc Angiogr Interv. 2022;1:100341. doi: 10.1016/j.jscai.2022.100341
15. Zeller T, Langhoff R, Rocha-Singh KJ, et al. Directional atherectomy followed by a paclitaxel-coated balloon to inhibit restenosis and maintain vessel patency: twelve-month results of the DEFINITIVE AR study. Circ Cardiovasc Interv. 2017;10:e004848. doi: 10.1161/CIRCINTERVENTIONS.116.004848
16. Rastan A, Brodmann M, Böhme T, et al. Atherectomy and drug-coated balloon angioplasty for the treatment of long infrapopliteal lesions: a randomized controlled trial. Circ Cardiovasc Interv. 2021;14:e010280. doi: 10.1161/CIRCINTERVENTIONS.120.010280
Advertisement
Advertisement

